

Introduction
A patient with diabetes, hypertension, and early kidney disease might see a primary care provider, an endocrinologist, a nephrologist, and a pharmacist in the same month. Each one makes decisions that affect the others. If those decisions aren’t shared, the patient ends up explaining their medication list from memory at every visit, tests get repeated because nobody knew they were already done, and small problems turn into hospital visits because nobody was watching for them between appointments.
That’s the gap care coordination is meant to close. It’s not a single task or a job title, though it often gets treated that way. It’s the ongoing work of making sure everyone involved in a patient’s care, including the patient, is working from the same information and moving toward the same goals.
This guide covers what care coordination means, how it differs from case management and care management, the activities and models that make it work, who’s involved, how it gets billed, and where practices most often struggle to make it happen consistently.
AI Summary
- Care coordination is the deliberate organization of patient care activities and information among everyone involved in a patient’s care, a definition established by the Agency for Healthcare Research and Quality (AHRQ).
- It’s often confused with case management and care management, but the three have different scopes, and understanding the difference changes how a practice staffs and structures the work.
- AHRQ’s framework identifies nine specific coordination activities and five broader approaches that, together, describe what care coordination actually requires in practice.
- Care coordination has defined, billable pathways under Medicare, including Chronic Care Management and Transitional Care Management, which matters for practices deciding whether to formalize a program.
- Most coordination failures happen at transitions between providers or settings, and at the technology gaps that keep information from following the patient.
What Is Care Coordination?
Before looking at models or billing codes, it helps to start with a definition that’s usable, not just accurate.
The Agency for Healthcare Research and Quality (AHRQ) defines care coordination as the deliberate organization of patient care activities between two or more participants, including the patient, involved in a patient’s care, in order to facilitate the appropriate delivery of health care services. That definition was built by combining more than 40 separate definitions found in the healthcare literature, because for a long time, nobody had settled on one.
That lack of a single agreed-upon definition isn’t just an academic detail. It’s part of why care coordination looks so different from one practice to another. A primary care clinic might treat it as something built into every visit. A hospital system might treat it as a formal department. A specialty practice might barely think about it until a patient falls through the cracks between two providers.
At its core, though, the goal is consistent everywhere: get the right information and the right care to the right people at the right time, so nothing about the patient’s treatment depends on luck, memory, or whoever happens to answer the phone that day.
Care Coordination vs. Case Management vs. Care Management: How They’re Different
These three terms get used almost interchangeably in day-to-day conversation, which causes real confusion when a practice is trying to decide who should own this work.
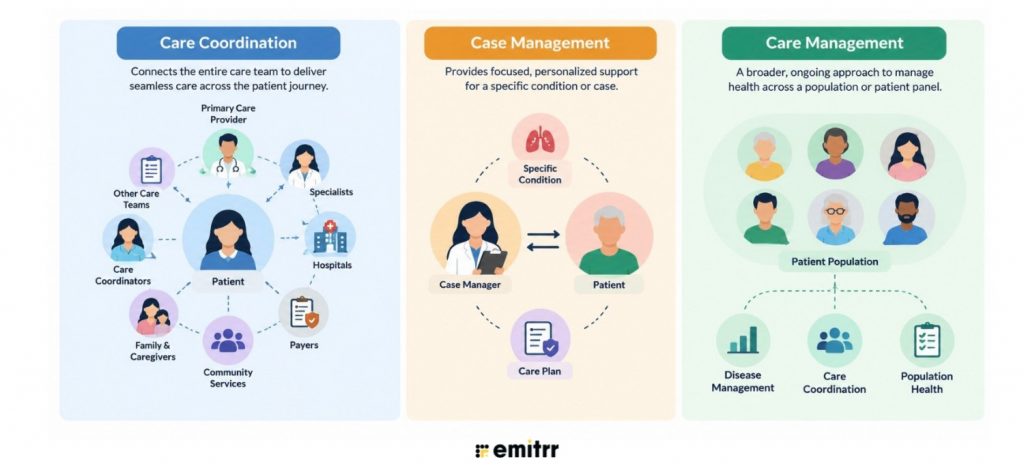
Care coordination is team-based and spans the whole care experience. It’s less about one person managing a case and more about making sure every participant, including specialists, primary care, and the patient, is working with the same information.
Case management is usually narrower. It typically centers on a single point of contact, often a nurse case manager, who follows a patient through a specific condition or episode, from assessment through discharge and follow-up. It tends to be more transactional than continuous.
Care management is the broader umbrella term. It includes both case management and disease management, and generally refers to the overall process of helping patients and their support systems manage medical, social, and mental health needs more efficiently.
Where things get genuinely confusing is at the role level. A care coordinator, a case manager, a patient navigator, and a care manager can all be doing overlapping work depending on the organization, and job titles aren’t standardized across healthcare settings.
Why Care Coordination Matters
It’s easy to treat care coordination as a nice-to-have until you see what happens without it.
Without coordination, patients get asked the same questions at every visit because nobody has their full history. Tests get duplicated because a result from three weeks ago wasn’t shared with the new provider. Medication lists conflict because two prescribers didn’t know about each other’s changes. Follow-up appointments get missed because nobody was tracking whether they happened.
These aren’t rare edge cases. They’re the default outcome of a fragmented system, and they show up most clearly for a few groups of patients:
- Patients with multiple chronic conditions, who are managing several providers and treatment plans at once
- Elderly patients, who often see the highest number of specialists and are most vulnerable to medication conflicts
- Pediatric patients with medical complexity, whose care spans specialists, schools, and therapies
- Behavioral health patients, whose care often crosses between physical and mental health providers who rarely communicate directly
The cost of poor coordination isn’t just clinical. Avoidable hospital readmissions and complications tied to fragmented care transitions represent a substantial and well-documented drain on healthcare spending. Programs that specifically target better coordination around discharge and follow-up have shown measurable reductions in readmission rates, which is part of why reducing hospital readmissions without increasing staff workload has become such a common priority for health systems and larger practices.

The Core Components of Care Coordination
AHRQ’s Care Coordination Measurement Framework breaks care coordination down into nine specific activities. They’re worth knowing in plain language, because they describe what actually has to happen, not just an abstract goal.
| Activity | What It Means in Practice |
| Establish accountability | Make clear who is responsible for each part of a patient’s care, and when that responsibility shifts to someone else |
| Communicate | Share information between everyone involved, both through direct conversation and through transferred records and data |
| Facilitate transitions | Ensure information and responsibility transfer cleanly when a patient moves between providers or settings |
| Assess needs and goals | Understand a patient’s physical, emotional, and functional needs, along with their own goals for care |
| Create a proactive care plan | Build a shared plan, jointly with the patient, that anticipates needs instead of only reacting to problems |
| Monitor and follow up | Track progress against the care plan and adjust it as circumstances change |
| Support self-management | Give patients the education and tools they need to manage their own care between visits |
| Link to community resources | Connect patients to services outside the healthcare system, such as social services or support programs |
| Align resources with needs | Match the level of coordination effort to how complex a patient’s or population’s needs actually are |
Common Models and Approaches to Care Coordination
Care coordination shows up through a handful of recognizable structural approaches, and most organizations use more than one at the same time.
The patient-centered medical home (or health care home) designates a primary source of care that acts as the coordinating hub for everything else, including specialists, community services, and the patient’s own preferences.
Care management, including case management and disease management, assigns dedicated staff or processes to help patients manage specific conditions or complex needs more efficiently.
Medication management and reconciliation focus specifically on catching and resolving conflicts in a patient’s medication list, particularly during transitions between care settings.
Team-based coordination models integrate separate providers, whether individuals, care teams, or entire organizations, into something that functions as a cohesive unit around the patient.
Health IT-enabled coordination uses electronic records, patient portals, and other digital tools to keep information moving between participants, rather than relying on phone calls and faxes.
Accountable Care Organizations (ACOs) take coordination further into a structural, financial model. Providers in an ACO share responsibility, and often financial risk, for a defined patient population, which creates a direct incentive to coordinate care well rather than treat it as optional.
The Care Coordination Process: How It Works
Care coordination isn’t a single event. It’s an ongoing process that repeats and adjusts as a patient’s needs change.
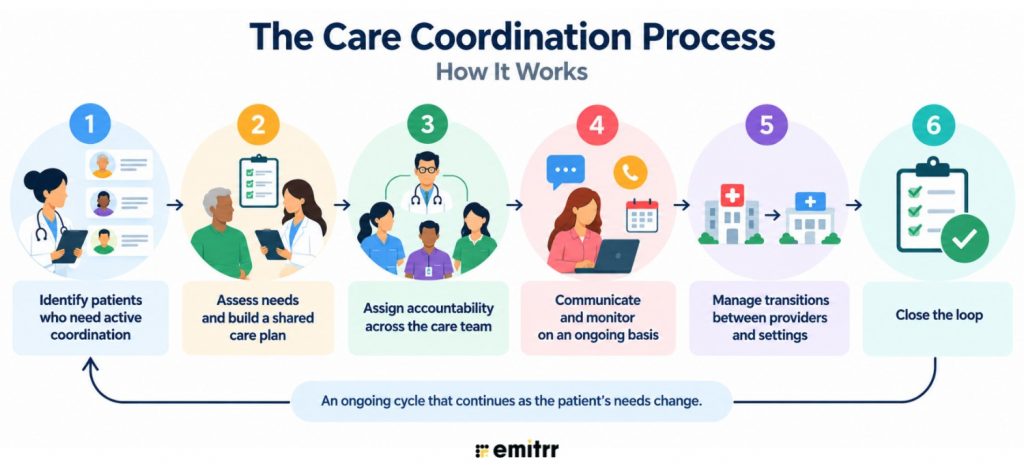
Step 1: Identify patients who need active coordination. Not every patient needs the same level of coordination effort. Practices typically prioritize patients with multiple chronic conditions, recent hospitalizations, or generally high clinical complexity.
Step 2: Assess needs and build a shared care plan. This includes the patient’s clinical needs, but also their goals, preferences, and any social or logistical barriers to following through on treatment.
Step 3: Assign accountability across the care team. Someone, whether a person or a defined process, needs to own each part of the plan.
Step 4: Communicate and monitor on an ongoing basis. Coordination isn’t a one-time handoff. It requires checking in, catching changes, and adjusting the plan.
Step 5: Manage transitions between providers and settings. This is where coordination is tested most directly, and where it fails most often if it isn’t deliberate.
Step 6: Close the loop. Confirm that the plan was actually followed and that the intended outcome was reached, rather than assuming it was.
This is a care coordination process in the fullest sense: not a checklist completed once, but a cycle that continues for as long as a patient needs coordinated care.
Transitions of Care: Where Coordination Breaks Down Most
If there’s one place where care coordination is tested hardest, it’s during a transition, when a patient moves from one provider or setting to another.
The highest-risk transitions tend to be:
- Hospital to home, where a patient leaves with new medications, new instructions, and often less support than the inpatient setting provided
- Emergency department to primary care, where the patient’s regular provider may not learn about the visit until much later, if at all
- Specialist to primary care, where findings and treatment changes need to make it back to the provider coordinating the patient’s overall care
A well-coordinated transition typically includes timely communication with the patient and their caregivers, medication reconciliation to catch conflicts introduced during the transition, a scheduled follow-up appointment, and clear education for the patient or caregiver about what to watch for.
This is also where transitional care management becomes a formal, billable service rather than just a best practice. Medicare recognizes the specific work involved in managing a patient’s first 30 days after a hospital, skilled nursing facility, or similar discharge, and reimburses for it accordingly. Organizations handling this window well typically treat it as a defined workflow rather than a loose set of intentions, tracking each discharged patient through contact, medication reconciliation, and a scheduled follow-up rather than hoping it happens. Building an effective post-discharge follow-up workflow that reduces readmissions largely comes down to making sure none of those steps depend on someone remembering to act on a patient’s file after they’ve already left the building.
Who’s Involved in Care Coordination
Care coordination touches more people than most practices initially account for, and each one plays a different role.
- The patient and their family or caregivers are the constant throughout the process, and often the only participants present at every stage.
- The primary care provider typically serves as the coordinating hub, even when specialists are doing much of the clinical work.
- Specialists and the broader clinical care team contribute expertise but rely on the hub to keep them informed of the full picture.
- Care coordinators, case managers, and nurse navigators carry much of the day-to-day coordination workload, particularly for complex patients. Building this role into a functioning workflow, rather than an informal responsibility layered onto existing staff, is often what separates practices that coordinate well from those that don’t.
- Community-based organizations and social services address needs outside the clinical system, such as housing, food access, or transportation.
- Payers increasingly play a direct role, particularly under value-based contracts that build coordination requirements directly into reimbursement.
Referral management is one of the more visible places where several of these participants intersect, since a referral intake is essentially a coordination handoff between two clinical parties.
Watch the 12 patient intake mistakes that can cost your practice time, revenue, and patient satisfaction, and learn how to avoid them.
How Care Coordination Is Billed and Reimbursed
Care coordination isn’t only a clinical best practice. Medicare has built specific, billable codes around it, which matters for any practice deciding whether to formalize a coordination program rather than treat it as unpaid, background work.
| Service | CPT Code(s) | What It Covers |
| Chronic Care Management (CCM) | 99490, 99439 | At least 20 minutes per month of non-face-to-face care coordination for patients with two or more chronic conditions |
| Transitional Care Management (TCM) | 99495, 99496 | Coordination during the 30 days following a hospital or facility discharge, with contact and follow-up visit requirements tied to complexity |
| Principal Care Management (PCM) | Separate code set | Similar to CCM, but for a single high-risk condition rather than two or more |
| Advanced Primary Care Management (APCM) | Separate code set | A newer, broader model bundling coordination-related services for primary care |
CCM requires an ongoing relationship with a patient managing multiple chronic conditions, while TCM is tied specifically to the discharge-to-follow-up window, with stricter timing requirements around patient contact and the required in-person visit.
Understanding these codes isn’t just useful for billing staff. It matters for anyone deciding whether a coordination program is financially sustainable, since the work of monitoring, following up, and managing care between visits can be reimbursed rather than absorbed as overhead. That distinction is usually what determines whether a practice ever moves past treating coordination as unpaid background work: once the monitoring and follow-up time is billed correctly, implementing a chronic care management program in your clinic stops being a cost center and starts paying for the staff time it requires.
Technology’s Role in Care Coordination
Technology doesn’t replace care coordination, but it’s very hard to do well without it, especially once a practice grows past the point where one person can hold the full picture in their head.
EHRs, patient portals, and health information exchange form the backbone of information transfer between providers. In theory, they let a specialist see what a primary care provider already knows, and vice versa.
In practice, interoperability barriers still get in the way constantly. Different systems use different data standards, some practices still rely on fax for critical handoffs, and even when systems can technically exchange data, the information often isn’t structured in a way that’s actually usable on the receiving end.
This is where HIPAA-compliant AI communication tools fit in as a distinct layer from the medical record itself. Secure messaging, automated outreach, and care team notifications don’t store the clinical data, but they keep the people involved in a patient’s care in sync in real time, which is a different problem than data storage. A patient who’s overdue for a follow-up, a caregiver who needs a callback, or a care team that needs to know a patient missed a specialist appointment all depend on communication reaching the right person quickly, not just existing somewhere in a chart. Practices dealing with fragmented communication hurting patient intake workflows are often running into a version of this same problem, just at an earlier stage of the patient relationship.
Technology can’t fix a coordination program that has no defined process behind it. But once a process exists, the right combination of unified communication and EHR-connected workflows is often what determines whether that process actually runs consistently or depends on staff remembering to follow up manually.
From routine communication to follow-ups, see what AI can handle for your front desk in this video
Common Care Coordination Challenges
Even practices that understand care coordination conceptually tend to run into the same operational obstacles.
- Fragmented systems and lack of interoperability, where information exists but doesn’t move cleanly between the people who need it
- Unclear ownership, where nobody is quite sure who’s responsible for following up on a given patient or task
- Time and staffing constraints, particularly for the non-billable portions of coordination work that fall outside CCM or TCM’s specific requirements
- Patient and caregiver confusion during transitions, especially when instructions come from multiple sources that don’t agree with each other
- Difficulty measuring whether coordination is actually working, which makes it hard to justify investing more in it
None of these problems are unique to any one practice size. Smaller practices often struggle with staffing and time, while larger, multi-location clinics tend to struggle more with consistency across sites and unclear ownership as the number of people involved grows.
Care Coordination in Practice: A Few Real-World Scenarios
Abstract definitions become clearer with concrete examples. Here are three common situations that show where coordination tends to succeed or fail.
A patient with multiple chronic conditions seeing several specialists. Without coordination, each specialist manages their piece in isolation, medication lists drift out of sync, and the patient becomes the only person who knows the full picture, if anyone does. With coordination, one provider or care team maintains the full medication list and care plan, and specialists are looped in on changes that affect their area.
A hospital discharge requiring medication reconciliation and a follow-up visit within days. This is the classic high-risk transition. Without a defined process, the patient may leave with unclear instructions and no scheduled follow-up, and small complications go unnoticed until they become emergencies. With a coordinated transitional care process, contact happens within days, medications are reconciled against what the patient was taking before admission, and a follow-up visit is already on the calendar before discharge.
A pediatric patient with complex needs coordinating between school, specialists, and therapies. These cases often involve participants entirely outside the traditional healthcare system. Without coordination, parents become the sole point of connection between every provider and service, which is exhausting and error-prone. With it, there’s a shared understanding of the child’s care plan across school staff, therapists, and medical providers, even though none of them report to each other.
How to Measure Care Coordination Effectiveness
Measuring care coordination requires looking beyond a single outcome. Effective coordination depends on how well patients understand their care, how consistently teams communicate, whether transitions and follow-ups are completed, and how reliably information moves across the care team. Reviewing these areas can help practices identify gaps that may affect patient experience, workflow efficiency, and continuity of care.
Want to assess how well your current process is working? Download the Care Coordination Effectiveness Checklist to self-assess your workflows, identify coordination gaps, and pinpoint areas that need improvement.
Best Practices for Building an Effective Care Coordination Program
Practices that coordinate care well tend to share a handful of habits, regardless of size or specialty.
- Start with a clearly defined care team and named accountability. Coordination fails fastest when it’s everyone’s job and therefore nobody’s.
- Standardize how information is captured and shared. Consistency matters more than sophistication, a simple process everyone follows beats a complex one that only works when the right person is available.
- Prioritize the highest-risk transitions first. Hospital discharges and specialist handoffs generally deserve attention before lower-risk touchpoints.
- Build in proactive, not just reactive, follow-up. Waiting for a patient to call with a problem means the coordination has already failed.
- Involve patients and caregivers as active participants. A care plan the patient doesn’t understand or agree with is unlikely to be followed.
- Track a small set of meaningful metrics from day one. Trying to measure everything usually means measuring nothing well.
For organizations scaling this across more than one location, the operational challenges compound, since consistency has to hold across sites that may have different staff, systems, and patient volumes. What works informally at a single site rarely survives that jump unchanged, which is why building care coordination workflows that scale across multi-location healthcare organizations usually means replacing the informal version with something standardized enough to hold up regardless of which location a patient walks into.
Key Takeaways
- Care coordination is the deliberate organization of patient care activities and information among everyone involved in a patient’s care, not a single task or job title.
- It differs from case management and care management in scope, though the three overlap significantly in practice, and titles aren’t standardized across organizations.
- AHRQ’s framework identifies nine specific coordination activities that describe what actually needs to happen, from establishing accountability to linking patients with community resources.
- Transitions between providers and care settings are where coordination breaks down most often, which is also where formal, billable services like transitional care management apply.
- Technology supports care coordination by keeping people in sync, but it can’t substitute for a clearly defined process with named accountability behind it.
FAQs
Care coordination is the ongoing work of making sure everyone involved in a patient’s care, including the patient, has the same information and is working toward the same goals, especially as the patient moves between providers or care settings.
Care coordination is team-based and spans a patient’s entire care experience across multiple providers. Case management is typically narrower, centered on a single point of contact managing a specific condition or episode from assessment through follow-up.
It varies by organization. Primary care providers often serve as the coordinating hub, while care coordinators, case managers, or nurse navigators handle much of the day-to-day work, particularly for complex patients. In smaller practices, this responsibility may be informally shared across existing staff.
Fragmented systems that don’t share information well, unclear ownership of coordination tasks, limited time and staffing for non-billable coordination work, and difficulty measuring whether coordination efforts are actually working.
Primarily through Chronic Care Management (CPT 99490, 99439) for patients with two or more chronic conditions, and Transitional Care Management (CPT 99495, 99496) for the 30 days following a hospital or facility discharge. Principal Care Management and Advanced Primary Care Management offer related, more specific reimbursement pathways.
Conclusion
Care coordination isn’t complicated in concept. It’s the discipline of making sure the right information reaches the right people at the right time, especially at the moments when a patient’s care crosses from one provider or setting to another. What makes it hard is doing that consistently, for every patient who needs it, without depending entirely on one person’s memory or bandwidth.
Practices that get this right usually combine a clearly defined process with the communication infrastructure to support it, so that coordination happens by design rather than by chance. Book a demo to see how a more connected communication workflow can support your care coordination efforts.


 4.9 (400+
reviews)
