

Introduction
Population health management gives healthcare organizations a structured way to improve health across a group, rather than addressing each encounter in isolation. It begins with a defined population, such as patients attributed to an accountable care organization, members covered by a health plan, or people receiving care from a health system. The organization then assesses shared needs, identifies variation in outcomes and access, and coordinates an appropriate response.
The purpose is not to replace individual clinical care. It is to connect that care to a strategy with measurable goals for outcomes, cost, quality, and equitable access. This population-level view can reveal patterns that are difficult to see when teams focus only on one patient or appointment at a time.
Understanding what population health management is also requires separating it from related concepts. Population health describes the outcomes of a group and how those outcomes are distributed. Population health management is the organized approach used to influence them. Public health and healthcare management may contribute to similar priorities, but they differ in scope and responsibility. This guide explains the population health management definition, its goals and components, and the continuous lifecycle healthcare organizations use to manage an accountable population over time.
AI Summary
- Population health management is a coordinated, data-informed strategy for improving health outcomes across a clearly defined group.
- A defined population is a group with established boundaries for which a healthcare organization accepts responsibility.
- The four primary goals of PHM are improving outcomes, reducing avoidable costs, strengthening care quality, and supporting equitable access.
- Core components include population identification, segmentation, risk stratification, care management, care coordination, patient engagement, preventive care, and performance measurement.
- The population health management lifecycle involves defining the population, assessing needs, segmenting people by risk, determining an appropriate response, engaging patients, monitoring outcomes, and refining the strategy.
What is Population Health Management?
Population health management, or PHM, is a strategic approach healthcare organizations use to improve outcomes across a defined group of people. It involves understanding the population’s shared health risks, care needs, access barriers, and gaps in recommended care, then organizing services and resources around those findings.
Instead of evaluating success only through individual visits or treatments, PHM examines what is happening across the full population. This broader view helps an organization identify patterns such as differences in preventive care completion, chronic condition outcomes, follow-up care, or healthcare utilization among groups with different needs.
Population health describes the outcomes an organization wants to influence. Population health management is the organized strategy used to influence them. Understanding why population health management matters provides further context on its role in modern healthcare delivery.
PHM should not be understood as:
- A standalone technology or software product
- A single patient outreach campaign
- An isolated quality-improvement project
- A replacement for individual clinical care
- A substitute for healthcare professionals
- A one-time review of population data
Technology may support population health management, but the strategy must begin with clear accountability, defined goals, coordinated responsibility, and an understanding of the population.
What Does “Defined Population” Mean in PHM?
A defined population is a clearly identified group for which a healthcare organization accepts responsibility. Its boundaries may be based on attribution, coverage, provider relationship, geography, condition, or risk. Establishing this denominator allows the organization to set goals and measure population-level outcomes.
Types of Populations Managed Through PHM
Population health management may apply to populations defined through care relationships, coverage arrangements, geography, health conditions, or risk.
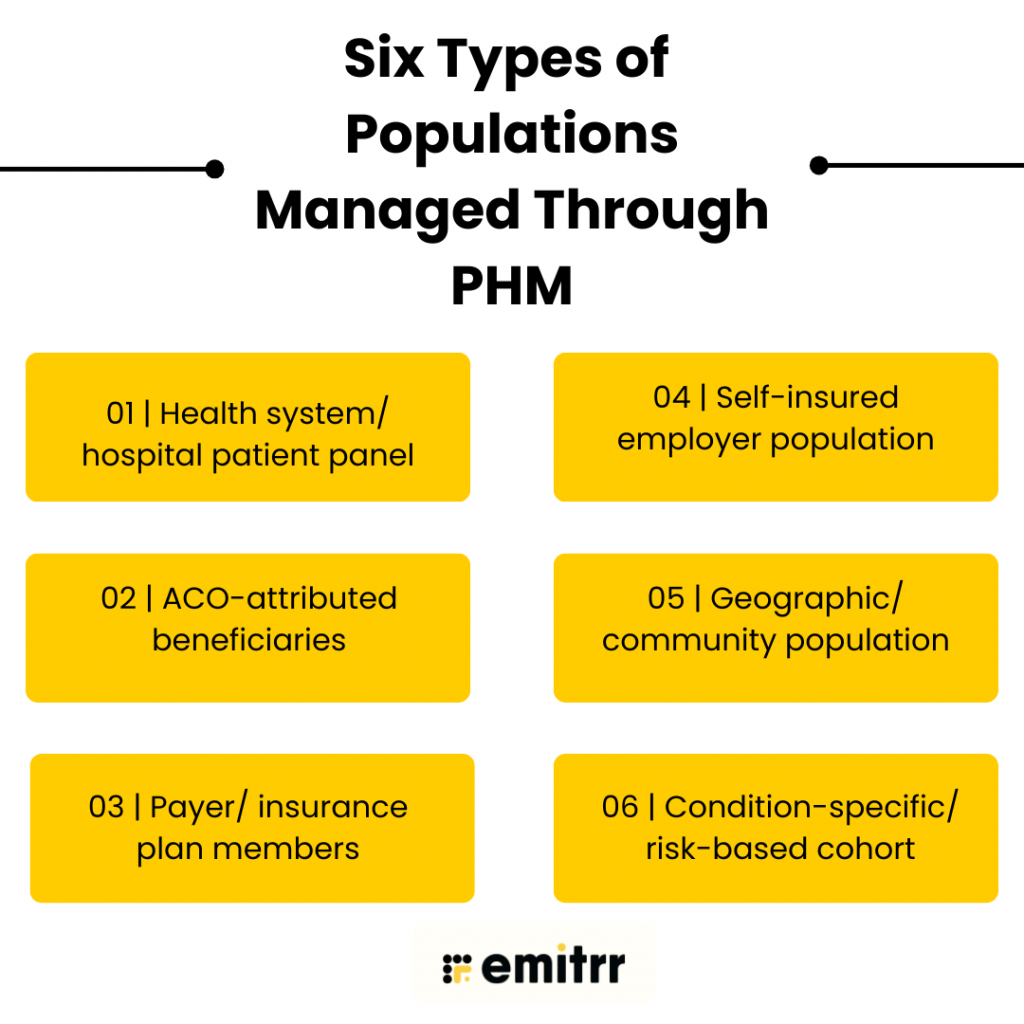
- Health system or hospital patient panel: Patients receiving care through a hospital, clinic network, or integrated health system.
- ACO-attributed beneficiaries: Individuals attributed to an accountable care organization under an applicable payment or care arrangement.
- Payer or insurance plan members: People enrolled in a health plan for which the payer monitors access, utilization, quality, and outcomes.
- Self-insured employer population: Employees and eligible dependents whose healthcare costs are covered through a self-funded employer plan.
- Geographic or community population: People living within a particular neighborhood, county, service area, or other geographic boundary.
- Condition-specific or risk-based cohort: People grouped according to a shared condition, identified care need, or relative level of risk.
A healthcare organization may manage several overlapping populations. A patient could simultaneously belong to a health system panel, a payer population, and a condition-specific group. Clear definitions help teams measure the correct denominator and avoid confusing one population’s results with another’s.
Explore these real-world examples of population health management to understand how healthcare organizations apply PHM across different populations and care priorities.
Population Health vs. Related Healthcare Concepts
Population health, population health management, public health, and healthcare management are sometimes used interchangeably in search results and marketing materials. Each concept has a different focus, scope, and form of responsibility.
Let’s understand some of those concepts –
Population Health Management vs. Public Health
Public health protects and improves health across communities and broader populations. Its responsibilities can include epidemiology, disease surveillance, health education, environmental health, prevention programs, emergency preparedness, and public policy.
Population health management usually operates within a more clearly attributed healthcare population. A health system, accountable care organization, or health plan may be responsible for a defined group and evaluate measurable outcomes within that group.
| Comparison Area | Population Health Management | Public Health |
| Typical population | Patients or members attributed to an accountable healthcare organization | Communities, regions, states, countries, or other broad populations |
| Primary focus | Coordinated care and measurable outcomes within a defined group | Disease prevention, health protection, policy, surveillance, and community health |
| Responsibility | Healthcare organizations, health plans, ACOs, and associated care teams | Government agencies, public health departments, and community partners |
| Connection to clinical care | Closely connected with healthcare delivery and organizational accountability | Extends beyond clinical care into social, environmental, regulatory, and policy factors |
The fields overlap around prevention, social determinants of health, health equity, and community needs. However, their boundaries and accountable organizations are not identical. Public health can address an entire community, including people who have no relationship with a particular healthcare organization. PHM generally starts with a population that an organization can identify and for which it has an established level of responsibility.

Population Health Management vs. Healthcare Management
Healthcare management focuses on operating healthcare organizations. It includes responsibilities such as staffing, finance, facilities, compliance, service capacity, and administrative performance.
Population health management focuses on improving health outcomes across an accountable population. Operational decisions may support that work, but efficiently running a healthcare organization does not automatically mean the organization has a PHM strategy.
| Comparison Area | Population Health Management | Healthcare Management |
| Primary objective | Improve outcomes across a defined population | Operate a healthcare organization effectively |
| Core responsibility | Population needs, care quality, access, coordination, and outcomes | Staffing, finance, facilities, compliance, and administration |
| Unit of focus | An accountable patient or member population | The healthcare organization and its operations |
| Measurement emphasis | Population-level outcomes and patterns | Organizational and administrative performance |
The two disciplines support each other. Healthcare management can provide the staffing, governance, and resources needed for PHM, while PHM can help organizational leaders determine where coordinated attention is required.
Population-level strategies also differ from care centered on one person’s needs. You can read the guide to population health vs. patient health management to understand this distinction in greater detail.
Goals of Population Health Management
The goals of population health management describe the outcomes an organization intends to influence across its defined population. They provide direction for the strategy and a basis for evaluating whether population needs are being addressed.
The four primary goals are improving health outcomes, reducing avoidable costs and utilization, strengthening care quality and consistency, and improving access and health equity. Their wider clinical, operational, and organizational impact is covered in our guide to the benefits of population health management.
Improve Population-Level Health Outcomes
The first goal is to improve health across the defined population, including how outcomes are distributed among different segments. This requires looking beyond isolated clinical encounters to determine whether disease burden, complications, or preventable deterioration are changing across the group.
Population-level assessment can also show whether progress is consistent. An overall improvement may conceal poorer outcomes within a particular location, demographic group, condition-based cohort, or risk segment. PHM therefore considers both aggregate outcomes and their distribution.
The purpose is not to guarantee a particular clinical result. It provides a structured approach to identifying population needs, coordinating appropriate care, and evaluating whether health patterns improve over time.
Reduce Avoidable Cost and Utilization
Population health management aims to reduce healthcare use that could reasonably be prevented through timely, appropriate, and coordinated care. This may include preventable emergency department visits, hospitalizations, readmissions, complications, or repeated services caused by fragmented care.
Not all utilization is avoidable, and lower utilization is not automatically better. Patients must still receive necessary services. The goal is to recognize patterns that may indicate delayed care, unmet needs, inconsistent follow-up, or preventable deterioration.
Cost is therefore considered alongside outcomes and quality. A strategy that lowers utilization while limiting appropriate access would not represent successful population health management.
Improve Care Quality and Consistency
Another goal is to reduce unwarranted variation in preventive, chronic, and follow-up care. People with similar needs should receive care aligned with established clinical and quality objectives, while individual decisions continue to reflect their circumstances.
Assessing performance across a population helps an organization see whether recommended care is reaching only some patients or locations. It can also show where transitions, follow-ups, or ongoing care are inconsistent.
Quality in PHM is not limited to whether a service occurred. It also concerns whether care was appropriate, timely, coordinated, and aligned with the organization’s defined objectives.
Improve Access and Health Equity
Population health management seeks to identify differences in access and outcomes between population segments. People may face unequal barriers related to geography, language, mobility, transportation, affordability, digital access, or other social and structural factors.
Aggregate results can obscure these differences. A population may appear to be progressing overall while a particular group remains less likely to receive appropriate care or experiences worse outcomes.
An equity-focused view asks how outcomes and access are distributed, not only whether the population average has improved. It helps an organization recognize where barriers differ, while the design of specific equity interventions belongs to a more detailed strategy.
Want to know how Emitrr AI agent improves patient communication? Watch this YouTube video now!!
Core Components of Population Health Management
The components of population health management are the foundational functions that connect an accountable population with organized care and measurable outcomes. They are interconnected rather than independent activities.
Population Identification and Segmentation
Population identification establishes who belongs to the accountable group. Segmentation then organizes that population into meaningful subgroups based on shared characteristics, conditions, risks, gaps, or support needs.
Identification creates a measurable denominator. Segmentation adds the detail needed to understand that people within the same population may require different levels or categories of support.
Risk Stratification
Risk stratification categorizes patients according to their relative level of risk and need. It helps distinguish people who may require intensive support from those whose needs may be addressed through routine preventive or ongoing care.
The categories depend on the purpose and context of the PHM strategy. Risk stratification supports prioritization, but it does not replace clinical judgment or determine care independently.
Care Coordination
Care coordination aligns responsibilities across providers, specialists, facilities, care settings, and other teams involved in a patient’s care. Its purpose is to reduce fragmentation and help each responsible participant understand the patient’s needs and next steps.
At the population level, coordination becomes especially important when many people receive care across different organizations or move between settings.
Patient Engagement
Patient engagement enables people to understand and participate in recommended care. Population-level goals depend partly on whether patients can make informed decisions, communicate their needs, and complete appropriate next steps.
Engagement does not mean transferring responsibility for outcomes to patients. It means recognizing that a PHM strategy must account for patient preferences, circumstances, understanding, and ability to participate.
Care Gap Management
Care gap management identifies when members of a population are missing recommended preventive, chronic, follow-up, or other appropriate care.
Care gaps provide a structured way to compare identified needs with care that has been received. Closing those gaps requires coordinated care-team action and patient participation, which are covered in greater depth in the care gap management guide.
Preventive Care Management
Preventive care includes recommended services intended to reduce future health risks or identify concerns earlier. Its role in PHM is to help an organization assess whether appropriate preventive care is reaching the defined population consistently.
Preventive needs vary according to individual circumstances and current clinical guidance. PHM supports population-level oversight while qualified healthcare professionals determine what care is appropriate for each patient.
Chronic Disease Management
Chronic disease management supports the ongoing needs of populations living with long-term conditions. These needs may extend across multiple appointments, providers, services, and periods of monitoring.
Within a PHM strategy, chronic disease management connects condition-based population priorities with continued individual care. It does not replace disease-specific clinical programs or treatment decisions.
Medication Adherence
Medication adherence can influence outcomes across populations in which prescribed treatment is part of ongoing care. PHM recognizes that missed, delayed, or discontinued medication use may reflect several factors, including side effects, affordability, access, understanding, or patient preference.
Adherence should therefore be considered in context and discussed with appropriate care professionals. It is not simply a matter of whether a patient followed instructions.
Performance Measurement
Performance measurement determines whether the goals of population health management are being achieved. It examines changes in outcomes, quality, access, utilization, and other measures relevant to the defined population.
Measurement also preserves accountability. It allows an organization to assess whether its current approach is appropriate, whether results differ across population segments, and whether priorities need to change.
(Read Full breakdown in the Care Management guide)
How Population Health Management Works (The PHM Lifecycle)
Population health management works through a continuous lifecycle that turns an identified population and its shared needs into coordinated care, patient participation, and measurable outcomes. Although organizations may use different terminology, the population health management process generally follows seven stages.
This section explains the conceptual lifecycle without prescribing specific technologies, outreach tactics, or operational workflows. Organizations ready to apply the framework can read our guide on how to implement population health management.
1. Define the Population
The lifecycle begins by establishing who belongs to the population. Its boundaries may be based on attribution, health plan coverage, a provider relationship, geography, a shared condition, or risk.
The organization must also clarify the responsibility it accepts for that group. A clear population definition creates the denominator needed to establish goals and evaluate outcomes.
2. Assess Population Needs
The organization assesses patterns involving health status, risk, healthcare utilization, access, and unmet needs across the population. This population-level view helps reveal needs that may not be apparent when individual encounters are considered separately.
The assessment establishes which needs and outcome differences require attention across the group.
3. Segment by Risk and Need
The population is divided into meaningful groups based on shared conditions, risks, care gaps, or support requirements. Segmentation recognizes that people within the same population may have substantially different needs.
These groups help the organization determine where different categories or levels of support may be appropriate without replacing individual clinical assessment.
4. Determine the Appropriate Response
Each population segment is matched with an appropriate category of care or support. The response should reflect the needs identified during assessment and the organization’s responsibility for the population.
This stage connects population-level findings with coordinated action. Qualified healthcare professionals remain responsible for determining what care is appropriate for each patient.
5. Coordinate Care and Patient Participation
Identified needs are connected with the providers, specialists, care teams, or services responsible for addressing them. Clear responsibility helps prevent important care needs from becoming disconnected as patients move between teams or settings.
Patients must also understand and participate in the recommended next step. Population-level planning can support better care, but it cannot produce completed care without patient participation.
6. Monitor Population Outcomes
The organization monitors whether health status, care patterns, quality, access, and utilization are changing across the defined population.
Monitoring should consider both overall results and differences between population segments. An improvement in the population average may conceal groups that continue to experience unmet needs or poorer outcomes.
7. Refine the PHM Approach
The organization uses what it learns to reassess population needs, risks, priorities, and responsibilities. Changes in health status, population membership, access, or outcomes may require the approach to be adjusted.
This stage leads back to the beginning of the population health management lifecycle. PHM is not a one-time program. It is a continuous process of defining responsibility, assessing needs, coordinating an appropriate response, monitoring results, and refining the strategy.
Technology can support different stages of this continuous process once the strategy and responsibilities are established. Our dedicated guide explains how AI is changing population health management without treating AI as the PHM strategy itself.
Key Takeaways
- Population health management is a strategy for improving outcomes across a defined population.
- A defined population requires clear boundaries, an established denominator, and organizational accountability.
- Population health describes a group’s outcomes and their distribution. PHM describes the organized approach used to influence them.
- The four central goals are improving health outcomes, reducing avoidable costs and utilization, strengthening care quality, and supporting equitable access.
- PHM includes interconnected components such as population identification, segmentation, risk stratification, care management, coordination, engagement, and performance measurement.
- The population health management lifecycle is continuous rather than a one-time initiative.
- The benefits, examples, implementation methods, technology, artificial intelligence, and software used in PHM require separate cluster guides.
FAQs
Population health management is a coordinated approach to improving health across a defined group. It helps healthcare organizations identify shared needs, organize appropriate care, engage patients, and measure population-level outcomes.
A population is a clearly identified group for which an organization accepts responsibility. It may be defined by provider relationship, health plan coverage, ACO attribution, geography, condition, or level of risk.
The main goals of population health management are to improve health outcomes, reduce avoidable costs and utilization, strengthen care quality and consistency, and improve access and health equity.
Core components include population identification, segmentation, risk stratification, care management, care coordination, patient engagement, care gap management, preventive care, chronic disease management, medication adherence, and performance measurement.
The process involves defining a population, assessing its needs, segmenting people by risk, determining appropriate support, coordinating care, engaging patients, monitoring outcomes, and refining the strategy.
Population health management usually focuses on patients or members attributed to a healthcare organization. Public health serves broader communities through prevention, surveillance, policy, epidemiology, and environmental health initiatives.
A population health manager helps define population priorities, coordinate teams, oversee population health programs, monitor performance, and evaluate whether the organization is meeting its quality, access, cost, and outcome goals.
There is no universally accepted set of four PHM pillars. A practical framework centers on population identification, coordinated care, patient engagement, and performance measurement, supported by segmentation and risk assessment.
An example is a health system identifying patients overdue for recommended preventive care, connecting them with the appropriate care team, supporting their participation, and measuring completion and outcomes across the population.
Conclusion
Population health management gives healthcare organizations a structured way to improve outcomes across a defined population. Its goals, interconnected components, and continuous lifecycle help organizations align population needs with coordinated care and measurable priorities.
Patient communication supports this strategy after populations, needs, and appropriate actions have been identified. Emitrr helps healthcare organizations automate patient outreach, manage two-way communication, and support participation in recommended care.
Want to strengthen population-level patient communication? Book a demo with Emitrr to see how automated outreach can support your PHM workflows.

 4.9 (400+
reviews)
