

Introduction
Most practices know roughly how many referrals they receive. Far fewer know how many of those referrals turn into completed visits. The difference is referral leakage, and it rarely announces itself. A referral doesn’t get rejected. It stops moving: a fax sits in a queue, a patient doesn’t pick up, an authorization surfaces late, and the patient eventually books somewhere else or never books at all.
Because nothing visibly breaks, referral leakage tends to surface only when revenue reports show fewer downstream visits than expected, or when a referring office quietly sends its patients elsewhere. Fixing it starts with seeing it: knowing what counts as leakage, where in the process it happens, what causes it, and how to measure it with numbers your team can actually act on.
This guide covers referral leakage in healthcare from the receiving practice’s point of view: the definitions that matter, what it costs, a stage-by-stage funnel, the most common causes, a practical way to do referral leakage tracking, the formulas behind referral conversion rate and referral completion rate, how to run a quick audit, and how to prevent referral leakage by fixing the right problem first.
What Is Referral Leakage in Healthcare?
Referral leakage in healthcare describes referrals that don’t end up where they were meant to. The term gets used in two different ways, and mixing them up leads to measuring the wrong thing.
| Term | Who Uses It | What It Measures | Who Owns the Fix |
| Network leakage | Health systems, ACOs, payers | Share of patients referred outside the network for care that could have stayed in | Network strategy, access, and referral program leaders |
| Referral abandonment | Specialty and multi-location practices that receive referrals | Referrals that never become a completed visit | Referral coordinators, front desk, and access leaders |
| Patient leakage | Health systems | Patients getting any care outside the system, whether or not a referral was involved | Service line and patient access leaders |
Which definition applies to your practice?
Independent and multi-location practices that receive referrals often deal with referral abandonment, where a referral arrives but the patient never completes a visit. Because many sources still use the term “referral leakage,” this guide uses both terms. Practices that also send referrals to other providers should track network leakage separately, since the owners and solutions differ. The receiving side is often more addressable because it follows a defined workflow with identifiable handoffs, which is where effective healthcare referral management can help practices identify and close gaps.
What Referral Leakage Costs
The direct cost is simple to estimate:
Lost revenue = referrals received x drop-off rate x average value per completed referral
Start with first-visit revenue only. Add follow-up visits and procedures if you can document them, but a conservative number is easier to defend and still makes the point.
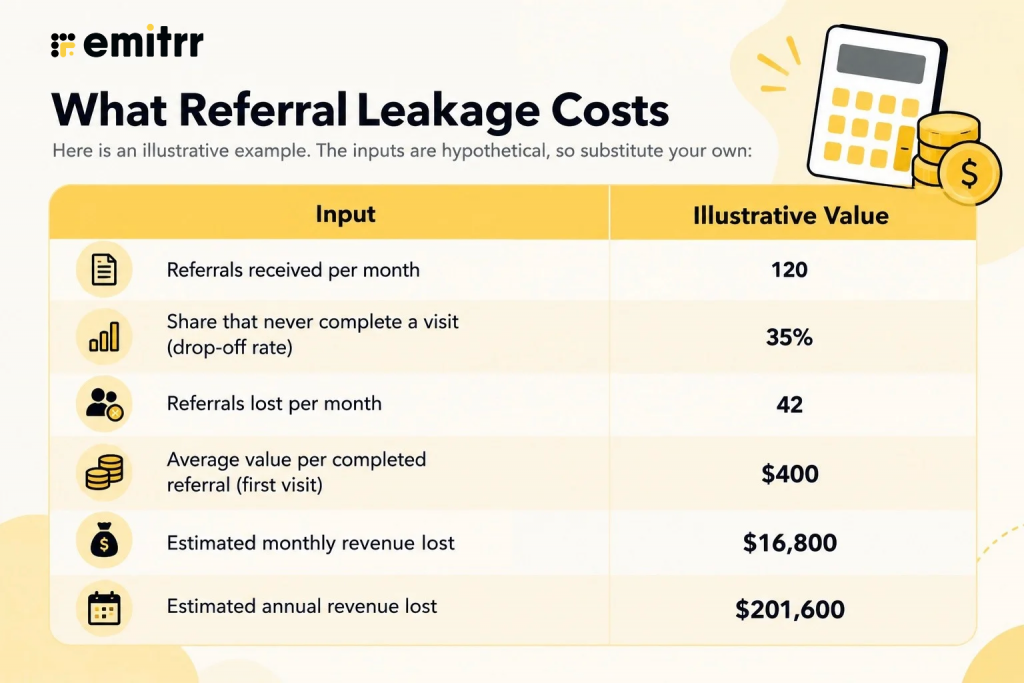
The downstream costs are harder to put on a spreadsheet but often matter just as much:
- Referrer relationships. A referring office that never hears what happened to its patient eventually stops sending them.
- Delayed care. Every week a referral stalls is a week the patient goes without the evaluation their provider ordered.
- Wasted intake effort. Staff spends time logging, confirming, and triaging referrals that ultimately do not convert, adding to the hidden cost of manual referral coordination.
Where Referrals Leak: The Referral Funnel Stage by Stage
Treating referrals as a funnel makes leakage visible. Each stage has its own failure mode and its own warning sign.
| Stage | What Leaks Here | Typical Warning Sign |
| Received | Referrals sitting in a fax tray, inbox, or voicemail box that nobody has opened | Referrals logged days after they were sent |
| Processed into the chart | Referrals never linked to a patient record, duplicates, lost attachments | Referring office asks “did you get it?” |
| Patient contacted | Slow first contact, unanswered calls, no second attempt | Long gap between receipt and first outreach |
| Scheduled | Patient reached but unable to find a workable time or provider | Referrals stuck in “contacted, not scheduled” |
| Authorized | Insurance or authorization problems found late | Cancellations or reschedules right before the visit |
| Visit completed | No-shows and cancellations that aren’t followed up | Scheduled visits that never turn into completed visits |
| Outcome sent back | Visit happens, but the referrer never hears about it | Referrer asks for a status or stops referring |
The final stage is less about immediate revenue and more about protecting the referring relationship. When practices make closing the referral loop a consistent part of the process rather than an occasional courtesy, they strengthen trust with referring offices and help maintain a steady flow of future referrals.
Referral Leakage Causes
Referral leakage causes tend to cluster in six groups. Most practices have a few of these, not all six, and the mix is different at every practice.

A few notes on how these play out:
- Process causes can compound quickly. A referral that arrives by fax, is manually re-entered, and then lands in a shared inbox can face multiple points of delay or loss before the patient is contacted. The difference becomes clearer when comparing fax-first referrals vs. digital-first referral workflows.
- Follow-up causes are usually the largest. Patient interest decays quickly, so a delay of days before first contact gives the patient time to book elsewhere.
- Access causes often get blamed for leakage that is really a matching problem. A referral can wait because no one noticed a qualified provider had an open slot at a different location.
- Patient-side causes are real, but many are recoverable with a clear message and an easy way to respond.
Patient intake gaps can contribute to referral delays and leakage. Watch this video to spot common intake problems and learn how to prevent them.
The Hidden Leak: Missed Calls and Voicemails From Referred Patients
Referral reports capture referrals that were received. They don’t capture the referred patient who called to schedule, reached voicemail, and never called back. For practices that depend on referrals for growth, this can be the largest leak and the least visible one.
Why it happens: front desks with thin coverage, especially one person per location, can’t answer every inbound call while checking in patients and handling other work. A referred patient who calls to book is usually motivated, but also usually has alternatives. A call that rolls to voicemail and isn’t returned quickly becomes a lost referral that never shows up in a referral report, because it was never matched to one.
You can estimate the size of this leak from call data:
- Export the call log for two to four weeks, including missed, abandoned, and voicemail calls.
- Match numbers to your referral list or new-patient records to separate referred callers from everyone else.
- Count unreturned calls and how long the typical callback takes.
- Estimate the loss: unanswered calls from referred or new callers x share who would have scheduled x average value per completed referral.
Even a rough estimate can show why missed call volume belongs in the referral leakage conversation. Practices looking to improve how quickly they respond can start by reviewing how to respond to a missed call and understanding how missed call text back software can help recover missed opportunities.

How to Track Referral Leakage
Referral leakage tracking depends on one thing: every referral needs a status and a timestamp at every stage. Without those, leakage is invisible until it shows up in revenue.
- Define consistent referral statuses. Use the funnel stages above (received, processed, contacted, scheduled, authorized, completed, outcome sent) so everyone describes referrals the same way.
- Timestamp every stage. Record when each status changed, not only the current status. Time between stages is where most leakage insight lives.
- Capture a reason code for every referral that doesn’t complete. “Patient unreachable,” “scheduled elsewhere,” “wait too long,” “authorization denied,” and “referral incomplete” tell you what to fix. “Closed” doesn’t.
- Segment the data. Break results out by referrer, specialty, location, and payer, since leakage is rarely uniform.
- Set a review cadence. A monthly review of the funnel and a weekly review of aging referrals is enough for most practices.
A minimal tracking sheet or dashboard needs these fields:

Referral Leakage Metrics and Formulas
A handful of metrics cover the whole funnel. Define each one precisely before you compare numbers across months or locations.
| Metric | Formula | What It Reveals |
| Referral processing rate | Referrals linked to a patient record within 24 hours / referrals received | Whether intake keeps up with volume |
| Time to first contact | Median hours from receipt to first outreach attempt | Speed of the earliest and often largest leak |
| Referral conversion rate | Referrals that become a scheduled visit / referrals received | How well you turn referrals into bookings |
| Referral completion rate | Completed visits / referrals received | The end-to-end result of the funnel |
| Referral abandonment rate | Referrals closed without a completed visit / referrals received | The leakage number, roughly 1 minus completion rate once open referrals are resolved |
| Time to appointment | Median days from referral received to first visit | Access and scheduling friction |
| Referred-patient no-show rate | No-shows / scheduled referred visits | Patient commitment and reminder effectiveness |
| Out-of-network leakage rate | Outbound referrals completed outside the network / total outbound referrals | Network leakage for practices that refer out |
| Closed-loop rate | Referrals with outcome sent back to the referrer / completed referrals | Referrer relationship health |
A note on benchmarks: Published targets for these metrics circulate widely, such as first contact within 24 hours, completion rates above 80 percent, and leakage rates below 20 percent. They vary by source, specialty, and how each source defines the terms, and many come from vendors. Use them as reference points only, and set your own baseline first. A practice that moves its own completion rate up by ten points has made real progress regardless of where it sits against a published number.
How to Run a Quick Referral Leakage Audit
You don’t need a new system to find your biggest leak. A sample of recent referrals is enough for a first answer.
- Pull a sample. Take 30 to 50 referrals received over the past one to three months, covering different referrers and locations.
- Trace each one to its outcome. Note every status change and date from receipt to completion or closure.
- Categorize every non-completion by the stage where it stopped and the reason.
- Rank causes by volume. Count how many referrals were lost at each stage and for each reason.
- Pick the top cause to fix first. Choose the one that is earliest in the funnel and largest in volume, then re-measure after the fix.
If a referral can’t be traced because its history is scattered across inboxes, spreadsheets, and call logs, that is itself a finding. It means leakage is invisible to you today, and tracking comes before fixing.
Example: Reading a Referral Funnel to Find the Biggest Leak
The following funnel is illustrative. It shows how to read a funnel, not what any specific practice should expect.
| Stage | Referrals Remaining | Lost at This Stage | % of Previous Stage |
| Received | 100 | n/a | n/a |
| Processed into the chart | 90 | 10 | 90% |
| Patient contacted | 66 | 24 | 73% |
| Scheduled | 55 | 11 | 83% |
| Authorized | 51 | 4 | 93% |
| Visit completed | 44 | 7 | 86% |
| Outcome sent back | 29 | 15 (of 44 completed) | 66% |
Overall, 44 of 100 referrals became completed visits, so abandonment is 56 percent. Reading the table:
- The biggest drop is between “processed” and “contacted” (24 referrals). That points to follow-up speed, missed calls, or no non-responder cadence, not to scheduling or authorization.
- Scheduling and authorization are smaller leaks (11 and 4). Worth fixing, but fixing them first would barely move the total.
- The “outcome sent back” gap doesn’t reduce completed visits, but it will eventually reduce referrals, so it belongs on the list after the contact stage.
The earliest, largest leak is also the one whose fix lifts every stage after it. That is why prioritization by position and size works.
How to Reduce Referral Leakage: Fixes by Cause
Knowing how to prevent referral leakage mostly means matching a fix to a cause, an owner, and a metric.
| Cause | Fix | Owner | Metric It Should Move |
| Fax and manual handling | Centralize intake into one queue with automatic logging and timestamps | Operations lead | Referral processing rate |
| Slow first contact | Send instant confirmation and start outreach within a set window | Referral coordinator | Time to first contact |
| Missed calls from referred patients | Capture and return every inbound call quickly, with text-back for unanswered calls | Front-desk lead | Referral conversion rate |
| No non-responder cadence | Set a follow-up sequence with escalation to a person after preset attempts | Referral coordinator | Referral conversion rate |
| Wrong provider or location match | Route by specialty, location, payer, and capacity rules | Referral coordinator, manager | Time to appointment |
| Late authorization discovery | Check eligibility and authorization at triage, not after scheduling | Coordinator or billing | Referral completion rate |
| Patient confusion or friction | Offer self-scheduling and plain-language messages about the referral | Access lead | Referral conversion rate |
| No status updates to referrers | Send automatic status updates and outcomes back to the referring office | Referral coordinator | Closed-loop rate |
Prioritization guidance: Start by addressing the earliest and largest source of leakage. If most referrals are lost before first contact, improving later-stage processes such as authorization will have limited impact.
Practices that want to address leakage without making a major system change can explore ways to reduce referral leakage without changing your EHR.
For practices using eClinicalWorks, eClinicalWorks integrations that reduce referral leakage can provide a more targeted approach.
Close the Gaps That Lead to Referral Leakage with Emitrr
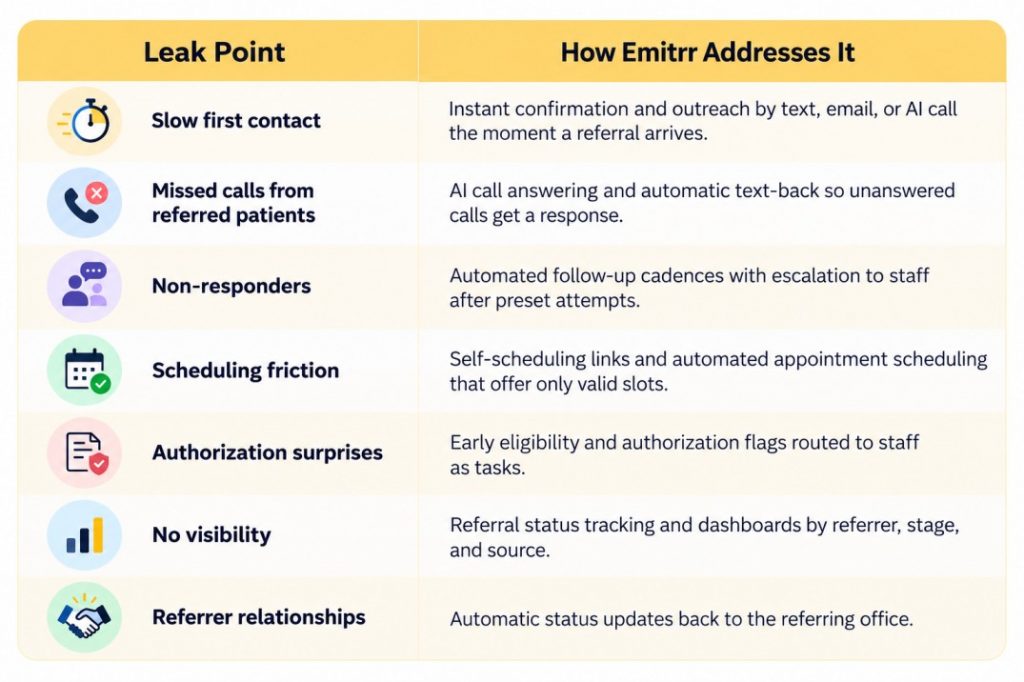
Referral leakage is mostly a speed and visibility problem, and both respond well to communication and workflow automation. The goal isn’t to remove people from the process. It’s to make sure no referral waits on someone remembering to act.
Emitrr works on the earliest leaks first, which is where most referrals are lost.
Every referral is captured and timestamped. Referrals from fax, web form, email, and phone land in one inbox, and a record and timestamp are created automatically, so processing rate and time to first contact can actually be measured.
Contact starts immediately. A branded confirmation goes to the referring provider and the patient right away. With two-way texting, either can reply to clarify details instead of waiting for a callback.
Missed calls stop disappearing. An AI answering service for healthcare can pick up calls that would otherwise go to voicemail, and missed call to text follow-up gives unanswered callers a quick way to continue the conversation.
Missing information is collected without a callback. An intake form or AI assistant asks the patient or referrer for what’s missing and stores it in structured fields.
Scheduling is easier to finish. Provider specialty, location, accepted panels, and capacity limits act as routing rules, so patients are offered only slots they qualify for. Patient self-scheduling lets them book on their own time, and where the system can write to the schedule, the booking completes automatically. Otherwise, staff get a one-click request to confirm.
Authorization problems surface early. Insurance and authorization status is checked in the workflow, and a task with exactly what’s needed goes to the right staff member if something is missing.
Non-responders get a cadence, then a person. Automated reminders, including AI calls and texts, go out on a set schedule. After a few attempts, the referral escalates to staff for manual outreach.
Referrers stay informed. Automated referral status notifications keep the referring office updated, and outcomes write back to the EHR automatically where supported or attach as structured PDFs where write-back isn’t available.
Leakage becomes measurable. Dashboards show referral volume, time to first contact, conversion, authorization delays, open tasks, and referral source performance.
Complex cases, payer disputes, and relationship-sensitive conversations with referring offices still require human judgment. Automation takes care of repetitive tasks and brings the situations that need staff attention to the surface. The same approach can also be applied to referral intake automation to reduce manual work earlier in the workflow.
Key Takeaways
- Referral leakage has two meanings: network leakage and referral abandonment. Practices that receive referrals mostly face abandonment, which is more directly fixable.
- Leakage is spread across a funnel, so tracking requires a status and timestamp at every stage plus a reason code for each referral that doesn’t complete.
- The most common referral leakage causes are slow first contact, manual and fragmented handling, scheduling friction, late authorization discovery, and missed calls from referred patients.
- The core metrics are processing rate, time to first contact, referral conversion rate, referral completion rate, referral abandonment rate, and time to appointment.
- Published benchmarks are reference points. Your own baseline matters more.
- A 30 to 50 referral audit usually reveals the biggest leak, and fixing the earliest, largest one first lifts every stage after it.
- Automation helps most with speed and visibility, while complex cases and relationships stay with people.
Frequently Asked Questions
Referral leakage in healthcare refers to referrals that don’t end up as completed care with the intended provider. For health systems, it often means patients referred outside the network. For practices that receive referrals, it means referrals that stall and never become a completed visit, also called referral abandonment.
Common causes include fax and manual handling, slow first contact, no follow-up cadence for non-responders, missed calls from referred patients, long waits or poor provider matching, late authorization discovery, patient confusion or cost concerns, and incomplete referrals or missing status updates for the referring office. Most practices have several at once, concentrated at different funnel stages.
Estimate the share of referrals that don’t complete, then apply value to it. Referral abandonment rate is referrals closed without a completed visit divided by referrals received. To estimate revenue lost, multiply referrals received by the drop-off rate and by the average value per completed referral. For network leakage, divide outbound referrals completed outside the network by total outbound referrals.
It varies by specialty, referral source, and how the term is defined. Some industry sources cite 80 percent or higher as a target, but those figures differ widely and are often vendor-published. The most useful benchmark is your own baseline measured consistently, and then your trend over time.
Referral leakage is the broader term and is used in two ways: patients leaving a network, and referrals that never complete. Referral abandonment is the narrower, practice-level version, describing a referral that stalls or is dropped before a visit happens. For practices receiving referrals, the two often describe the same problem.
Start by tracking every referral by stage with timestamps and reason codes. Run a short audit to find the earliest, largest leak, then match a fix to that cause: centralized intake, faster first contact, missed-call coverage, a follow-up cadence, better provider matching, early authorization checks, or automatic status updates to referrers. Re-measure after each change.
Conclusion
Referral leakage is less a single failure than a series of small ones spread across the funnel: a delayed fax, an unreturned call, a missing authorization, a patient who never got a second message. That’s what makes it easy to overlook and worth measuring. Practices that track each referral by stage, assign reason codes to every non-completion, and fix the earliest, largest leak first tend to see their referral conversion rate and referral completion rate improve without needing more referrals to arrive.
The numbers don’t have to be perfect to start. A short audit and a simple tracking sheet will show where referrals are going, and automating the follow-up and visibility work keeps them from slipping again.
Book a free demo and see how Emitrr helps your team respond faster, follow up consistently, and track every referral to completion.


 4.9 (400+
reviews)
